
 Save
If you are over 60 and take metformin, a proton pump inhibitor, an H2 blocker, or several long-term prescriptions, vitamin B12 is worth bringing up at your next medication review. The practical question is not whether B12 is dangerous with these medicines for most people. It is whether the medicine pattern, age-related absorption changes, diet, and symptoms make low B12 more likely or easier to miss. The NIH Office of Dietary Supplements explains that vitamin B12 depends on normal stomach and intestinal absorption, and that metformin and gastric acid inhibitors can affect B12 status in some people (NIH ODS).
Why B12 deserves attention after 60
Vitamin B12 helps the body make red blood cells and supports normal nerve function. It is found naturally in animal foods, including fish, meat, poultry, eggs, and dairy, and it is also added to some fortified foods. The same nutrient can be abundant in the diet and still become a concern when absorption is reduced. That distinction matters after 60 because stomach acid, intrinsic factor, intestinal health, surgery history, and long-term medicines all shape how well B12 from food becomes available to the body. The NIH notes that B12 from fortified foods and supplements is already in a freer form than B12 bound to food proteins, which is one reason clinicians may look at both diet and absorption rather than diet alone (NIH ODS).
Older adults can also have overlapping explanations for tiredness, numbness, balance changes, memory concerns, or weakness. Those symptoms do not automatically mean low B12, and they should not be self-diagnosed from an article. They are, however, the kind of details worth mentioning when a clinician is already reviewing long-term prescriptions. MedlinePlus lists long-term metformin use and long-term use of antacids or other heartburn medicines among possible contributors to B12 deficiency anemia, alongside digestive conditions, stomach or intestinal surgery, dietary restriction, and other causes (MedlinePlus).

The medicine groups most worth reviewing
The most common B12-related medication discussion after 60 usually centers on two everyday categories: metformin and acid-reducing medicines. Other medicines may also matter in individual cases, so a full medication list is more useful than focusing on one pill. Bring prescription medicines, over-the-counter products, and supplements into the same conversation. A practical review can include:
- Metformin: widely used for blood sugar management and repeatedly linked with lower B12 levels in some long-term users.
- Proton pump inhibitors: acid-reducing medicines such as omeprazole, esomeprazole, lansoprazole, pantoprazole, and related drugs.
- H2 blockers: acid-reducing medicines such as famotidine and similar drugs.
- Other long-term medicines: some guidance also flags medicines such as colchicine and certain antiseizure medicines as factors clinicians may consider.
- Supplement labels: B12 may appear alone, in a multivitamin, in a B-complex product, or in fortified foods, so duplicate products can confuse the picture.
Metformin has one of the clearest official safety messages. The United Kingdom Medicines and Healthcare products Regulatory Agency advises that reduced B12 levels are now considered a common side effect in people taking metformin, with risk increasing in people using higher amounts for longer periods and in those with additional risk factors. The same safety update advises checking B12 levels when symptoms suggest deficiency and considering periodic monitoring in patients with risk factors (GOV.UK MHRA).
Metformin: what to ask, not what to stop
Metformin remains an important prescribed medicine for many adults, and a B12 conversation should not be treated as a reason to stop it without medical guidance. The better question is whether your clinician already has a monitoring plan. Ask whether your duration of use, age, diet pattern, digestive history, or symptoms make B12 testing reasonable. If you already have nerve symptoms, balance changes, anemia, or persistent fatigue, say so plainly rather than assuming they are normal aging. MedlinePlus drug information for metformin also advises patients to tell their doctor about low B12 levels and to share all prescription, nonprescription, vitamin, nutritional supplement, and herbal products they use (MedlinePlus metformin).
Acid-reducing medicines: the stomach acid connection
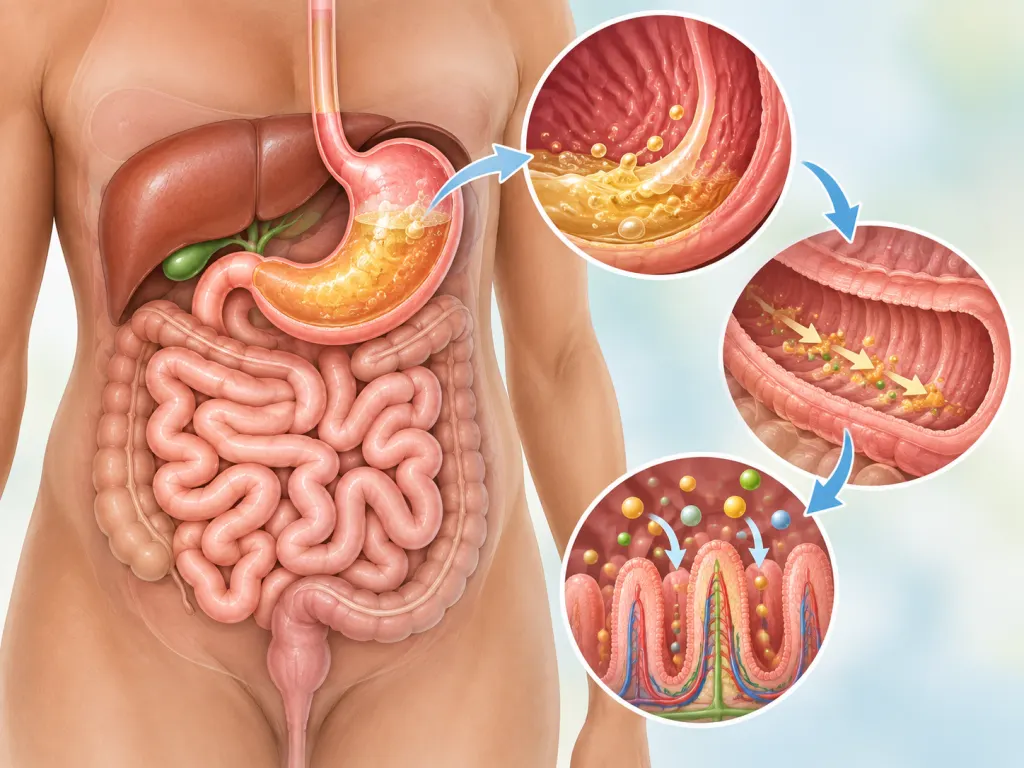
Proton pump inhibitors and H2 blockers reduce stomach acid. That can be helpful for reflux or other conditions when used appropriately, but stomach acid also helps release B12 from food proteins. Mayo Clinic explains that blocking stomach acid can keep the body from taking in enough B12 from food, and that daily use for a year or more has been linked in some studies with B12 deficiency (Mayo Clinic). This does not mean every person taking an acid reducer needs the same plan. It does mean long-term use deserves periodic review, especially when the medicine began years ago and has simply stayed on the list.
Why age changes the conversation
After 60, B12 status sits at the intersection of food, absorption, medicine use, and other medical history. A person eating regular servings of animal foods may still have absorption trouble. A person eating little meat or dairy may have an intake issue as well as an absorption issue. A person taking metformin plus a proton pump inhibitor may have more than one reason for a clinician to look closer. The NIH summarizes several groups at risk for B12 inadequacy, including older adults, people with certain stomach or intestinal conditions, people who have had some gastrointestinal surgeries, and people taking certain medicines for long periods (NIH ODS).
This is also why the answer is rarely as simple as buying a supplement and moving on. Low B12 can come from pernicious anemia, intestinal conditions, surgery history, dietary restriction, medication effects, or combinations of those factors. The right follow-up may depend on test results and the suspected cause. In its evidence review for vitamin B12 deficiency guidance, NCBI Bookshelf summarizes that evidence suggested metformin, proton pump inhibitors, and H2 receptor antagonists can be risk factors, while also noting limitations and possible confounding in the acid-reducer evidence (NCBI Bookshelf). In plain terms: the signal is important, but context matters.
Symptoms worth mentioning clearly
B12 deficiency can be quiet, gradual, and nonspecific. Some people have no obvious symptoms at first. Others notice changes that overlap with many other conditions. MedlinePlus lists possible symptoms including fatigue, lightheadedness, pale skin, shortness of breath with exertion, a swollen or red tongue, numbness or tingling in the hands and feet, balance problems, concentration trouble, irritability, and confusion in severe cases (MedlinePlus). Because these symptoms have many possible causes, the most useful step is to report them accurately: when they started, whether they are worsening, whether they are one-sided or both-sided, and whether they affect walking, sleep, eating, or daily tasks.
Questions to bring to a medication review
A short written list can make the appointment more productive. Consider asking: Have I been on metformin or an acid reducer long enough that B12 monitoring makes sense? Do my symptoms fit any pattern that should be checked? Should my complete blood count, B12 level, or related markers be reviewed? Could any medicine on my list still be necessary but due for reassessment? Are my supplement labels duplicating ingredients? If I eat little animal food, should that change the plan? These questions help keep the focus on individualized care rather than internet rules.

How clinicians may check B12 status
Testing is more nuanced than a single number in isolation. The NIH explains that serum or plasma B12 is commonly used to assess B12 status, while methylmalonic acid may help confirm deficiency in some borderline situations; it also notes that methylmalonic acid can be influenced by kidney function and may be higher in older adults (NIH ODS). MedlinePlus lists tests that may be used in evaluation, including a complete blood count, serum B12, methylmalonic acid, homocysteine, and tests related to intrinsic factor or parietal cell antibodies when clinically appropriate (MedlinePlus).
That testing context matters because anemia is not always the first clue, and neurologic symptoms can occur without anemia. It also matters because some lab markers are affected by kidney function, inflammation, recent supplements, and the laboratory method used. If you have already started a B12 supplement before testing, tell the clinician. That detail can change how results are interpreted. The goal is not to chase a perfect number, but to connect symptoms, risk factors, test results, and a plan that matches the likely cause.
Food and supplements: useful, but not a one-size answer
Food sources of B12 include fish, meat, poultry, eggs, dairy products, fortified breakfast cereals, and fortified nutritional yeast. For some older adults, fortified foods or supplements may be easier to absorb than B12 bound to food proteins, but a clinician may still need to determine why levels are low. Cochrane reviewed randomized trials comparing oral B12 with intramuscular B12 for deficiency and found low-quality evidence that oral and intramuscular approaches had similar effects on blood B12 levels in the small studies reviewed, while also emphasizing limited evidence and the need for better trials (Cochrane). That is a useful discussion point, not a self-treatment rule.
A practical plan for adults over 60
The safest practical plan is simple: keep an accurate medication and supplement list, notice persistent symptoms, and ask for a B12 conversation during routine care if you take metformin, a long-term acid reducer, or several medicines. Do not quietly stop a prescribed medicine because of B12 concerns. Do not assume a supplement will explain or fix fatigue, tingling, balance trouble, or confusion. And do not let a normal-looking diet end the conversation if symptoms and risk factors remain. B12 is a small nutrient with a surprisingly detailed pathway through the body; after 60, reviewing that pathway with a qualified clinician is often the most sensible move.
Wrap-Up
B12 concerns after 60 are best handled as part of a medication review. Metformin and acid-reducing medicines are the two groups most often connected with lower B12 status, and other medicines or medical history can add context. The useful next step is not panic or stopping medicine, but a clear conversation with a doctor or pharmacist about symptoms, duration of use, diet pattern, testing, and monitoring.
Frequently Asked Questions
- → Which common medicines are most often discussed with B12 after 60?
Metformin and long-term acid-reducing medicines are the main groups to review. Acid reducers include proton pump inhibitors and H2 blockers. Some other medicines may also matter, so it is best to review the full medication and supplement list with a doctor or pharmacist.
- → Should I stop metformin or a heartburn medicine if I am worried about B12?
No. Do not stop a prescribed medicine on your own. Ask whether your duration of use, symptoms, diet pattern, and medical history make B12 testing or monitoring appropriate.
- → Can low B12 happen even if I eat meat, eggs, or dairy?
Yes. B12 intake and B12 absorption are different issues. Some people eat B12-containing foods but absorb less because of stomach, intestinal, surgical, or medication-related factors.
- → What symptoms should I mention at an appointment?
Mention persistent fatigue, lightheadedness, numbness or tingling, balance changes, concentration changes, a sore or swollen tongue, shortness of breath with exertion, or new weakness. These symptoms can have many causes, so they need clinical review rather than self-diagnosis.
- → Is a B12 supplement enough to solve the concern?
Not always. A supplement may be part of a clinician's plan, but the cause matters. Testing, medical history, and the suspected reason for low B12 can affect whether food changes, oral supplements, injections, or other follow-up is appropriate.
References
This content was developed and refined using reliable sources.
- https://ods.od.nih.gov/factsheets/Vitaminb12-HealthProfessional
- https://www.gov.uk/drug-safety-update/metformin-and-reduced-vitamin-b12-levels-new-advice-for-monitoring-patients-at-risk
- https://www.medlineplus.gov/ency/article/000574.htm
- https://www.medlineplus.gov/druginfo/meds/a696005.html
- https://www.mayoclinic.org/diseases-conditions/gerd/expert-answers/heartburn-meds-and-b12/faq-20348628
- https://www.ncbi.nlm.nih.gov/books/NBK603365
- https://www.cochrane.org/evidence/CD004655_oral-vitamin-b12-compared-intramuscular-vitamin-b12-vitamin-b12-deficiency





